
The fastest path to ready-to-play hospital training videos is this: use AHRQ TeamSTEPPS modules for team communication and simulation, CDC just-in-time clips for low-frequency emergencies, WA Health’s clinical incident management series for incident response, and MedlinePlus for anatomy and procedure explainers. Commission custom assets when any of these conditions apply:
- Your unit runs a local protocol that differs from the national standard shown in the video
- The scenario requires in-situ realism (your ward layout, your equipment, your ambient noise)
- Patient or staff consent for identifiable footage is needed and cannot be obtained from a third-party source
- The video will be consumer-facing or branded for your hospital
- A high-risk, low-frequency procedure has no existing vetted resource that matches your clinical governance requirements
If none of those conditions apply, the free resources below will cover most of your programme needs today.
Key takeaways
The most effective hospital training video programmes combine free, vetted public resources for universal competencies with custom in-situ assets for locally specific scenarios, always paired with facilitator guides and clinical sign-off.
| Point | Details |
|---|---|
| Start with free vetted resources | AHRQ TeamSTEPPS and CDC STRIVE cover team communication, PPE, and incident management at no cost. |
| Commission custom assets for local specificity | Use custom production when local protocols, in-situ realism, or patient consent requirements cannot be met by existing resources. |
| Never deploy a video without facilitator materials | A facilitator guide with debrief questions and a participant worksheet turns a clip into a complete learning intervention. |
| Match format to learning goal | Microlearning (1–7 minutes) for single skills; full simulations (20–60+ minutes) segmented into 5–10 minute teachable units for team training. |
| True Care Media for custom production | True Care Media delivers fixed-fee custom hospital training videos with clinical review, facilitator materials, and LMS-ready delivery for Australian hospitals. |
Table of Contents
- Where are the best ready-to-play hospital training videos?
- Which sources and hosts can you actually trust?
- How do you plan and script an effective clinical training video?
- What does a solid E-E-A-T production checklist look like?
- How do you deploy videos and measure whether they work?
- What are the accessibility and legal requirements in Australia?
- What video format and run time should you use?
- Custom hospital training videos: True Care Media can help
- Sources
Where are the best ready-to-play hospital training videos?
The catalogue below groups vetted clinical training videos by topic. Each entry notes the learning objective, approximate runtime, and availability for Australian users.
Team communication and leadership
AHRQ TeamSTEPPS Module 2 (Team Leadership) covers situational awareness, briefing and debriefing, and mutual support. The full-length simulation runs approximately 20 minutes and ships with downloadable facilitator guides and segmented clips designed for discussion-led learning rather than passive viewing. Freely available; US-produced but the communication principles map directly to Australian clinical governance expectations.
AHRQ TeamSTEPPS Module 3 provides a full simulation scenario with facilitator guides and pre-cut segments of roughly 5–10 minutes each, purpose-built for debrief-led team training. Both Module 2 and Module 3 are the closest thing to a complete off-the-shelf team-training package available without cost.
Infection prevention and PPE
The CDC STRIVE curriculum combines technical PPE and hand-hygiene training with a business-case module designed to engage ward managers and executive sponsors. STRIVE’s evidence shows that the best infection-prevention outcomes come from pairing technical competency training with facilitator materials, not from standalone video clips. Freely available; requires an internet connection or download for offline use.
Radiological emergencies and just-in-time training
The CDC just-in-time radiological training video runs 17 minutes and links triage priorities to patient scenarios. It is the clearest example of the just-in-time format done well: short, scenario-linked, and signposted for a low-frequency, high-stakes event. Freely available; ideal for emergency department and radiology staff.
Clinical incident management
WA Health’s clinical incident management training videos cover incident investigation principles and response processes. Produced by a state health authority, they carry direct policy alignment for Australian hospitals. Publicly accessible; check whether your state health service has an equivalent series before defaulting to WA Health’s version.
Anatomy and procedure explainers
MedlinePlus health videos and tools hosts a broad collection of anatomy, body-system, and procedure explainer videos. They work best as reference material for clinician instruction or as pre-reading before a simulation session, not as standalone competency training. Freely available; no facilitator materials supplied.
Moving and handling, surgical teams
NSW Health and other state health services publish clinical skills video hubs covering manual handling, aseptic technique, and surgical team procedures. Search your state health intranet or the relevant state health education portal directly, as these are often hosted behind staff login rather than on public-facing sites.
Which sources and hosts can you actually trust?
Not every clinical video on YouTube has been through a clinical review cycle. Before you play anything to staff, check the host against this list.
- AHRQ (Agency for Healthcare Research and Quality): — US federal agency; TeamSTEPPS content is evidence-based, peer-reviewed, and updated. Module content was last reviewed July 2023. Facilitator guides and worksheets are included.
- CDC (Centres for Disease Control and Prevention): — STRIVE and just-in-time modules are produced to federal public-health standards. Both include supporting materials.
- WA Health and state health service hubs: — Produced under Australian clinical governance frameworks. Content reflects local policy and terminology. Check your own state’s equivalent before using another state’s version.
- MedlinePlus (US National Library of Medicine): — Reliable for anatomy and general health explainers; not a source for procedural competency training. No facilitator materials.
- Hospital YouTube playlists: — Useful for awareness and orientation, not for competency sign-off. Verify the publishing organisation, check the upload date, and confirm the content matches your local protocol before use.
Before deploying any external video, run a brief clinical governance check: confirm the content aligns with ACSQHC standards and your hospital’s own policy, note the evidence citations the video references, and flag any protocol differences to staff in the facilitator debrief. The CDC STRIVE approach of pairing technical content with a business case is worth borrowing here: brief your ward manager on why the video was selected and what local adaptations apply.
Pro Tip: Prefer videos that ship with a facilitator guide and participant worksheet. A video without supporting materials is a clip, not a learning intervention. The AHRQ TeamSTEPPS modules are the benchmark: every segment comes with debrief questions and an assessment checklist.
How do you plan and script an effective clinical training video?
Start with a measurable learning objective tied to a local competency standard or audit criterion. “Staff will be able to don and doff PPE in the correct sequence without prompting” is a usable objective. “Staff will understand PPE” is not.
Once the objective is set, choose the scenario type that matches your assessment method.
Microlearning demo (1–7 minutes): Single skill, single objective. Assessed by direct observation or a short knowledge check. Best for refreshers and just-in-time use.
Short demonstration (8–20 minutes): Procedure overview with multiple steps. Assessed by competency checklist. Suits annual mandatory training modules.
Full simulation (20–60+ minutes): Team scenario with multiple roles and decision points. Assessed by facilitator observation and structured debrief. Requires segmenting for classroom use (see Section 8 below).
A workable script structure for any of these formats runs: opening learning objective stated on screen, clinical context established in the first 60 seconds, step-by-step demonstration with on-screen labels, facilitator prompt cards at natural pause points, and a short assessment checklist at the close. Keep the opening objective to one sentence. If you need two sentences, the scope is too broad.
For facilitated sessions, write three to five debrief questions into the run-sheet before filming. Questions like “What did the team leader do at the 90-second mark that changed the outcome?” are more useful than “What did you notice?” because they direct attention to the specific behaviour the video was designed to demonstrate.
Best-practice staff training frameworks also recommend polling staff for training needs before scripting, offering continuing education units where possible, and collecting post-session feedback to improve future iterations.
Pro Tip: Break any script longer than 10 minutes into named segments with timestamps before you go to production. Retrofitting segment breaks after filming is expensive and often means re-shooting transition shots.
What does a solid E-E-A-T production checklist look like?
E-E-A-T (Experience, Expertise, Authoritativeness, Trustworthiness) is not just a search-engine concept. For hospital training videos, it maps directly to clinical governance requirements. Require every item below from any supplier, and apply the same standard to internally produced assets.
Production roles and sign-off
- Script writer: drafts scenario, learning objectives, and facilitator prompts
- Clinical reviewer (subject-matter expert): verifies clinical accuracy against current evidence and local protocol; signs off before filming
- Producer/director: manages shoot logistics, consent, and technical quality
- Accessibility reviewer: confirms closed captions, transcript accuracy, and accessible player compatibility
- Clinical governance lead: final sign-off against ACSQHC standards and hospital policy
Mandatory content elements
- Learning objective stated on screen within the first 30 seconds
- Evidence citations in on-screen notes or a linked reference list
- Facilitator guide with debrief questions, timing, and assessment checklist
- Participant worksheet with pre- and post-activity prompts
- Closed captions (WCAG 2.1 AA minimum) and downloadable transcript
- Consent documentation for any identifiable patient or staff footage
- Metadata formatted for LMS integration (SCORM or xAPI where required)
- Secure hosting option for sensitive clinical content
The AHRQ TeamSTEPPS modules meet nearly all of these criteria and serve as a practical benchmark when briefing a production supplier.
Facilitator worksheet template
A usable worksheet covers: learning objectives (one sentence each), pre-session preparation for participants, video runtime and segment timestamps, three to five structured debrief questions, a competency observation checklist, and a space for participant self-assessment. Keep it to one page. Two pages and facilitators stop using it.
Staged review cycles
Run three review cycles: script review before filming, rough-cut review with the clinical lead, and final review for captions and accessibility. Define acceptance criteria for each stage in the production brief so the supplier knows what “approved” means before they invoice.
In-situ simulation research from AHRQ shows that filming in the actual clinical environment, capturing real equipment, layout, and ambient sound, improves team dynamics and protocol uptake. If your scenario involves unit-specific procedures, an in-situ shoot is worth the additional coordination.
How do you deploy videos and measure whether they work?
Deployment method should follow the learning goal, not the other way around.
LMS module with quiz: Best for mandatory compliance training where completion and knowledge-check scores need to be recorded. Pair with a short pre- and post-quiz. Track completion rate and score distribution, not just completion alone.
Facilitated in-service with debrief: Best for team simulation and communication training. The video is the trigger for discussion, not the training itself. Use the TeamSTEPPS facilitator guide format: watch a segment, pause, debrief, watch the next segment.
Mobile just-in-time clip: Best for low-frequency, high-stakes events. The CDC radiological training video is the model: 17 minutes, scenario-linked, accessible on a phone at the point of need.
Unit huddle with short segment: Best for refreshers and awareness. Pull a 3–5 minute segment, play it at the start of a shift huddle, ask one debrief question.
For evaluation, track these metrics: completion rate, pre/post knowledge-check scores, competency observation results before and after training, incident-report trends in the relevant clinical area over the following quarter, and staff confidence ratings collected immediately after the session. Polling staff on training needs before and after a programme cycle, as recommended by healthcare training best-practice frameworks, also gives you the qualitative signal that numbers alone miss.
Well-designed just-in-time training can also reduce the time staff spend away from the bedside, which matters for nursing home staff efficiency and applies equally to acute ward settings where pulling staff for lengthy in-services carries a real opportunity cost.

What are the accessibility and legal requirements in Australia?
Australian hospitals must meet both clinical governance and legal obligations when using or producing training videos. Work through this checklist before any video goes live.
- Captions and transcripts: Closed captions are required for all staff-facing training content under the Disability Discrimination Act 1992. WCAG 2.1 AA is the minimum standard. Auto-generated captions do not meet this standard without human review.
- Accessible player: Confirm the video player supports keyboard navigation and screen-reader compatibility.
- Patient consent: Any footage featuring an identifiable patient requires written informed consent, documented and stored in line with the Privacy Act 1988 and your hospital’s own consent policy. This applies even to de-identified footage where re-identification is plausible.
- Staff consent: Identifiable staff appearing on camera require written consent. Clarify whether consent covers internal use only or extends to external distribution.
- Secure hosting: Sensitive clinical content should be hosted on a platform with access controls, not on a public YouTube channel. Confirm your LMS or hosting platform meets your hospital’s data security requirements.
- Licence verification: Before using any third-party video, confirm the licence explicitly permits your intended use (internal training, public distribution, or LMS embedding). AHRQ and CDC content is generally in the public domain for educational use, but verify the specific terms for each asset.
- ACSQHC alignment: Cross-reference video content against the relevant Australian Commission on Safety and Quality in Health Care standards before deploying. This is particularly important for clinical incident management and infection prevention content.
What video format and run time should you use?
The right format depends on what you need staff to be able to do after watching, not on what is easiest to produce.
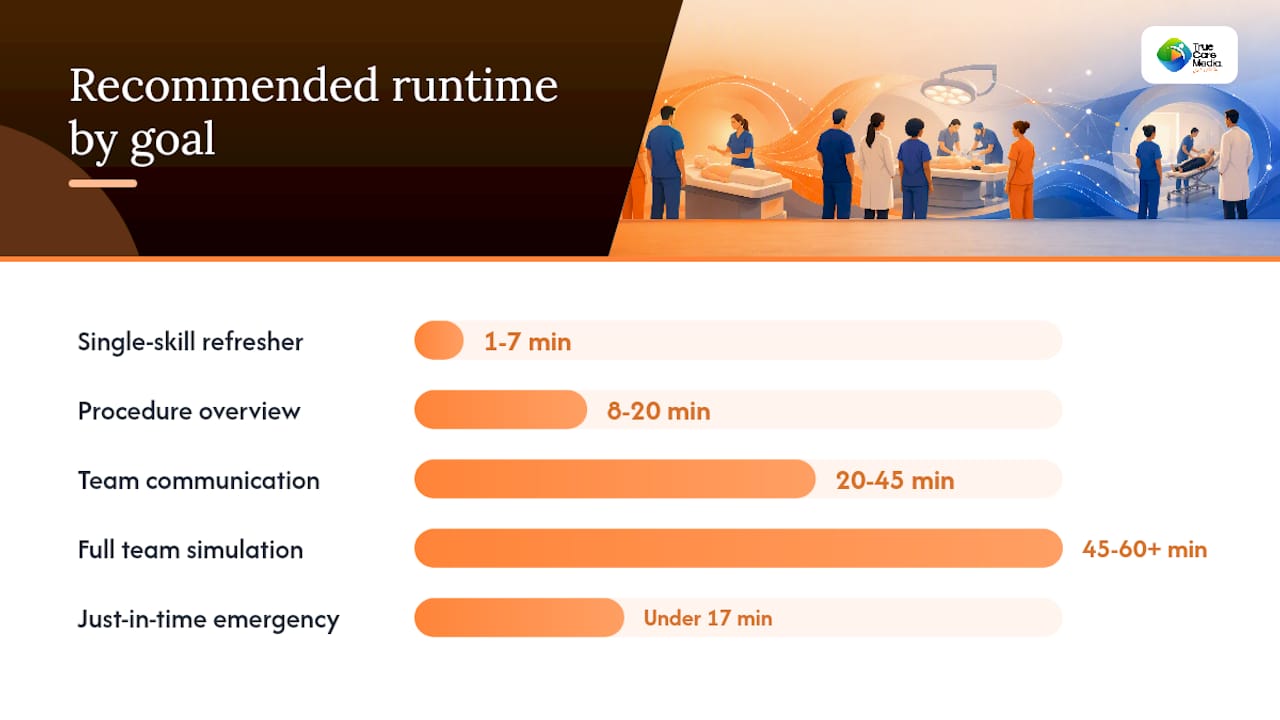
| Training goal | Recommended format | Ideal run time | Segmenting guidance |
|---|---|---|---|
| Single skill refresher | Microlearning demo with on-screen checklist | 1–7 minutes | No segmenting needed |
| Procedure overview | Talking-head demo with overlaid captions and step labels | 8–20 minutes | Split at natural procedure phases |
| Team communication training | Multi-camera simulation with facilitator pause points | 20–45 minutes | 5–10 minute segments with debrief prompts |
| Full team simulation | Multi-camera, multi-role scenario | 45–60+ minutes | Timestamp every decision point; 5–10 minute teachable units |
| Just-in-time emergency reference | Short scenario-linked clip | Under 17 minutes | Single segment; no split needed |
For full simulations, add a timestamp index to the facilitator guide so educators can jump directly to the segment relevant to their debrief focus. A 45-minute simulation with five named segments and five sets of debrief questions is a complete learning intervention. The same footage without timestamps and questions is just a long video.
Procedure explainer videos work best with a talking-head clinician, overlaid step labels, and a downloadable checklist. Multi-camera capture is worth the additional cost for team simulations because it lets the facilitator replay the same moment from different angles during debrief.
Why a blended approach works better than either option alone
The instinct to choose between ready-made videos and custom production is understandable, but it is usually the wrong frame. The hospitals that get the most out of their training investment use vetted public modules for universal competencies (team communication, PPE, incident management) and commission custom assets for the scenarios where local specificity is non-negotiable: your resuscitation trolley layout, your patient-transfer protocol, your ward’s specific cultural and language considerations.
The gap that custom production fills is not quality. AHRQ and CDC produce excellent material. The gap is relevance. When a nurse watches a simulation filmed in a US emergency department with unfamiliar equipment labels and a different escalation pathway, the cognitive load of translating the scenario to their own context reduces the training transfer. An in-situ video filmed on their ward, with their colleagues, using their equipment, removes that translation step entirely.
The other thing most educators underestimate is the facilitator guide. A video without structured debrief questions is a passive experience. The same footage with a well-designed worksheet becomes a conversation that surfaces local practice gaps the video alone would never reveal. Commissioning a custom video without budgeting for the facilitator package is one of the most common and most costly mistakes in clinical education production.
Custom hospital training videos: True Care Media can help
True Care Media produces custom hospital training videos for Australian private hospitals, allied health clinics, and care providers, from script development and clinical review through to in-situ filming, facilitator materials, and LMS-ready delivery. The difference from a generic production house is the clinical governance layer: every project includes a clinical reviewer sign-off cycle and a facilitator guide built to the same standard as the AHRQ TeamSTEPPS benchmark.

If your unit needs a custom simulation, a procedure explainer, or a full training package with participant worksheets and assessment checklists, the process starts with a briefing conversation. Bring your learning objectives, your local protocol documents, and any existing video assets you want to build on. True Care Media will scope the project, advise on format and run time, and provide a fixed-fee quote. You can also request a sample facilitator pack to see the standard before committing.
Get in touch via Truecaremedia to request a briefing or sample pack.
Sources
Direct links to the authoritative hosts and hubs referenced throughout this article.
- Module 2 Training Simulation Video (Full). Content last reviewed July 2023. Agency for Healthcare Research and Quality
- CDC/STRIVE Infection Control Training | Infection Control | CDC
- Health videos and tools | MedlinePlus
- Clinical incident management training videos
AHRQ and CDC are the only free sources that consistently supply facilitator guides and participant worksheets alongside the video asset. For Australian-specific content, WA Health is the most accessible public-facing state hub, but most state health services maintain internal libraries that are richer and more locally relevant.